Last updated: September 22, 2026
See How Rhythm360 Extends Monitoring Beyond The Hospital
Telemetry units admit patients who need continuous rhythm surveillance but do not require ICU-level one-to-one nursing. Common admission diagnoses include:
Telemetry also supports non-cardiac conditions that carry cardiac risk. Accepted indications include acute stroke, drug overdose, and substantial electrolyte abnormalities. Patients recovering from major surgery who have cardiac risk factors, those receiving QT-prolonging medications, and those on anticoagulant drips may also be placed on telemetry.
Telemetry is not indicated for rate-controlled atrial fibrillation that is clinically stable, chronic PVCs, or non-cardiac chest pain. Between 30% and 90% of noncritical care telemetry use is inappropriate or continued longer than recommended, and patients monitored without a clear indication rarely have arrhythmias identified that change management.
A telemetry unit and an ICU represent distinct levels of care, with different monitoring intensity, staffing ratios, and interventions.
The hospital acuity ladder runs from general medical-surgical floors at the bottom to telemetry, then step-down or progressive care units (PCU), and finally the ICU at the top. General med-surg floors check vital signs every six hours and do not monitor heart rhythm continuously. Telemetry floors provide continuous rhythm surveillance with nurse-to-patient ratios of 1:4 to 1:5. Step-down units run 1:3 to 1:4 with full bedside monitors at every bed. The ICU provides 1:1 or 1:2 nursing with invasive hemodynamic monitoring and mechanical support capability.
The Cardiac ICU is reserved for patients with cardiogenic shock, advanced respiratory failure, life-threatening arrhythmias, or hemodynamic compromise requiring vasoactive medications, invasive monitoring, or mechanical circulatory support. Patients with acute decompensated heart failure without cardiogenic shock may be managed in step-down or telemetry settings with appropriate monitoring and escalation pathways.
The key distinction between telemetry and step-down is what each unit can handle. Telemetry units manage patients who need rhythm observation but are not on medications requiring constant dose adjustments. Step-down units carry sicker patients who may need ventilator support, continuous blood pressure medications requiring frequent titration, or insulin drips. When a telemetry patient stabilizes, the care team may downgrade them to a general floor. If they deteriorate, they move up to step-down or the ICU.
Cardiac telemetry offers powerful rhythm surveillance with clear limits that patients and new nurses should understand.
Telemetry can detect arrhythmias, abnormal QT intervals, and electrocardiographic changes suggestive of myocardial ischemia. It cannot identify non-cardiac causes of symptoms, diagnose structural heart disease, or catch intermittent events that occur between monitoring periods. The American Heart Association’s Practice Standards acknowledge that there is no Level A evidence supporting the benefit of telemetry.
False alarms are a documented and significant problem. As many as 90% of monitor alarms in some settings may be false, most often triggered by patient movement, loose electrodes, or electrical interference from nearby equipment. Patient movement during monitoring can generate muscle artifact that distorts the ECG waveform and can be mistaken for a true arrhythmia.
The clinical consequence of this alarm volume is alarm fatigue. Only 10–20% of clinical alarms require any clinical intervention. The high frequency of non-actionable alerts can condition caregivers to distrust or ignore subsequent signals, which contributes to delayed responses to life-threatening arrhythmias. Conditions requiring longer-term or implantable monitoring, such as infrequent paroxysmal arrhythmias, may not be captured during a standard telemetry admission at all.
Anxiety and psychological stress produce real, measurable changes in heart rate and rhythm that are visible on a telemetry tracing.
Anxiety activates the sympathetic nervous system and releases adrenaline, which accelerates the heart rate and can trigger premature beats. On the monitor, that pattern may appear as sinus tachycardia, frequent premature atrial or ventricular contractions, or rate variability. These are genuine physiological responses. The care team interprets these findings in the context of the patient’s full clinical picture, including their emotional state, medications, and underlying diagnosis. Patients who notice their heart rate climbing during a stressful moment on the unit can inform their nurse, who will factor that context into any rhythm interpretation.
Patients sleep with the telemetry transmitter in place. The transmitter is small and lightweight, and most patients carry it in a pouch or set it on the bedside table within lead-wire reach. Electrode patches stay on the chest through the night. Nurses check the skin under each patch daily for irritation, and patches are replaced every 24 to 48 hours to maintain signal quality and skin integrity. The monitoring station continues to display the patient’s rhythm throughout the night, so the care team is watching even while the patient sleeps.
Patients can generally use a cellphone while wearing a telemetry transmitter. External electrical sources, including other medical equipment in the patient’s room, can interfere with the ECG signal during cardiac telemetry monitoring. Some hospitals ask patients to keep phones a short distance from the transmitter to reduce the risk of electromagnetic interference distorting the tracing. The specific guidance varies by unit and equipment model, so patients should ask their nurse for the policy on their particular floor.
A typical day on a telemetry unit follows a structured rhythm that most patients find less disruptive than they expect.
The morning starts with a nursing assessment covering cardiac and respiratory status, a review of overnight rhythm strips, vital signs, weight measurement for heart failure patients, and medication administration. Vital signs are checked every four hours or more frequently depending on the patient’s condition. Monitoring occurs more often than on a general floor but not continuously at the bedside the way ICU patients are monitored.
Mobility remains a core part of the day. Most telemetry patients can walk, sit in a chair, eat meals, and move around, but must stay within the transmitter’s signal boundary. Patients needing tests elsewhere in the hospital are switched to a portable monitor for transport. Showering typically requires a brief disconnection from the monitor. For patients with a history of dangerous rhythms, a nurse or aide may remain nearby during that window.
Alarms occur throughout the day and shape much of the unit’s pace. Many alarms are technical, such as a loose electrode patch from repositioning or a low transmitter battery, rather than clinical emergencies. The telemetry technician at the central station identifies the alarm type and notifies the bedside nurse, who assesses the patient directly. Patients often hear alarms from neighboring rooms as well as their own, and the care team’s calm, systematic response to each alert is the norm.
Physicians and cardiology teams round once or more daily to review rhythm strips, adjust medications, and reassess the need for continued monitoring. If the rhythm has been stable for a sufficient period, the team may discontinue telemetry and transfer the patient to a general floor. If the condition worsens, the patient moves to a higher-acuity setting. Length of stay on telemetry ranges from about 24 hours after a low-risk procedure to several days for complex medication titration or arrhythmia management.
Telemetry is demanding, and experienced nurses describe it that way. The unit demands continuous rhythm surveillance while also requiring nurses to manage four to five complex cardiac patients per shift. Nurses can expect 10,000–15,000 steps per 12-hour shift, frequent IV access challenges, physical resuscitation participation, and the sustained alertness required to manage rhythm changes that can occur at any time.
The learning curve feels steep but stays manageable with support. Most hospitals run an 8- to 16-week orientation for experienced RNs, and longer residency programs of 12 to 18 months for new graduates. Orientation typically covers a dysrhythmia recognition course, cardiac medication training including heparin and antiarrhythmic drip protocols, precepted clinical shifts with a gradual patient load increase, and competency check-offs for 12-lead ECG interpretation and code blue participation. Most new graduates find basic rhythm recognition becomes reflex by month three, and managing four to five patients with varying cardiac conditions becomes manageable by month six.
Telemetry also serves as direct non-ICU preparation for critical care roles. The rhythm interpretation skills, cardiac pharmacology knowledge, and emergency response experience built on a telemetry unit translate directly to the ICU, the cath lab, and the electrophysiology lab. Renown Health telemetry nurse Kayla Lafoon advises new nurses that the pressure to know all the answers fades with experience: “Over time, I’ve learned the value of asking for help, collaborating and recognizing that no one has all the answers.”
The same monitoring workload that makes telemetry demanding also creates opportunities for support from remote platforms. Remote cardiac monitoring can offload alert review and documentation so bedside nurses can focus on direct care.
Explore Remote Monitoring For Your Practice
Telemetry practice is shifting from reactive alarm response toward proactive, centralized monitoring governance. The problem driving that shift is well documented. The Joint Commission recorded 98 alarm-related sentinel events between 2009 and 2012, 80 of which resulted in patient death, and the FDA documented 566 alarm-related deaths from 2005 to 2010. The root cause is a lack of intelligent triage.
Machine learning models trained on large inpatient arrhythmia datasets distinguish clinically significant rhythm changes from artifact more accurately than conventional threshold-based alarm systems. They reduce false-positive alarm rates without sacrificing sensitivity to true events. AI-assisted predictive monitoring that analyzes trends in heart rate variability and ST-segment morphology to anticipate deterioration before it manifests as a discrete alarm represents a promising direction, though large-scale randomized validation remains ongoing.
Centralized monitoring architectures are also being redesigned. A timed escalation pathway, in which a critical alarm not acknowledged at the central station within 30 seconds auto-escalates to the primary bedside nurse, then a buddy nurse, then the charge nurse, and finally the rapid response team, is proposed by the Safer Telemetry Architecture framework as an evidence-informed hypothesis for reducing the risk of alarms being trapped at an unmanned station, though the framework has not yet been empirically validated as a complete system.
Readers who want a deeper look at the monitoring technology itself can review electrode systems, transmitter types, central station architecture, and the clinical evidence behind specific monitoring protocols in RhythmScience’s Cardiac Telemetry Monitoring: Complete Hospital Guide.
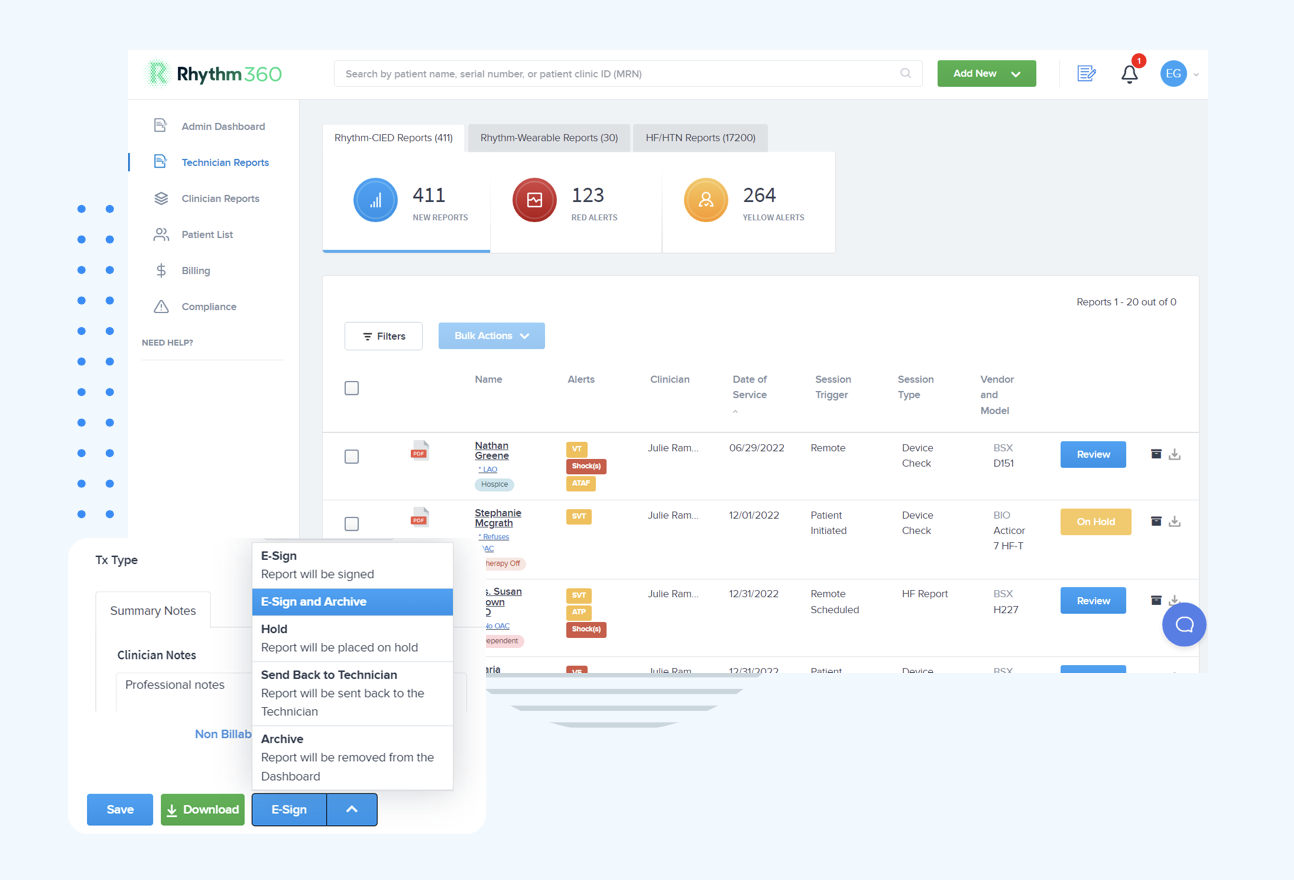
The next frontier extends continuous monitoring beyond the hospital floor entirely. Rhythm360 by RhythmScience is a vendor-neutral, HIPAA-compliant, cloud-based remote patient monitoring platform that unifies data from all major cardiac device manufacturers, including Medtronic, Boston Scientific, Abbott, and Biotronik, into a single dashboard. AI-powered alert triage filters non-actionable noise and prioritizes clinically significant events, with optional 24/7/365 oversight by certified cardiac technicians. Practices using Rhythm360 have achieved up to an 80% reduction in critical alert response times and up to a 300% increase in revenue generation through optimized CPT code capture, improved staff efficiency, and the addition of new RPM service lines. Other platforms in this space include Murj, Implicity, Rhythm Management Group, and Octagos.
Talk To Our Team About Continuous Monitoring
Length of stay on telemetry depends on the reason for monitoring and how quickly the rhythm stabilizes. Some patients remain for about 24 hours after a low-risk procedure, while others stay several days for complex medication titration or arrhythmia management. The care team reviews your rhythm and overall status each day and discontinues telemetry once continuous monitoring no longer adds clear benefit.
Patients should report any new palpitations, chest discomfort, shortness of breath, dizziness, or sudden fatigue right away. Sharing the exact time, what you were doing, and how long the sensation lasted helps the nurse match your symptoms to the telemetry tracing. That context allows the team to decide whether the rhythm change requires medication adjustment, further testing, or a higher level of care.
Most telemetry systems allow limited movement within a defined signal range. Patients can usually sit in a chair, walk in the room, and sometimes walk in the hallway if the signal remains strong. Staff will explain the boundaries for your specific unit and equipment. If you need to travel off the unit for tests, the team connects you to a portable monitor or arranges supervised transport.
A trained telemetry technician or monitor tech usually watches the central station, which displays rhythms for multiple patients at once. The technician reviews alarms, checks for changes in rhythm, and calls the bedside nurse when something needs attention. Nurses also review rhythm strips during assessments and rounds, so multiple team members keep eyes on the tracings.
A cardiac telemetry unit provides continuous rhythm surveillance for middle-acuity patients who are stable enough to leave the ICU but still need close monitoring. Clear expectations about who telemetry admits, what a day on the floor looks like, and what the monitors can and cannot detect reduce fear for patients and guesswork for new nurses.
Monitoring technology continues to evolve. Alarm fatigue, centralized monitoring gaps, and the limits of threshold-based alert systems are well-documented challenges that AI-assisted triage and intelligent escalation pathways are beginning to address inside the hospital. Beyond the hospital floor, platforms like Rhythm360 extend that continuous monitoring capability to patients with cardiac implantable electronic devices and chronic conditions, unifying data from all major device manufacturers into a single, AI-powered dashboard with optional oversight by certified cardiac technicians. Practices using this type of remote monitoring platform have reported up to an 80% reduction in critical alert response times and up to a 300% increase in revenue generation through optimized CPT code capture, improved staff efficiency, and new RPM service lines.
Talk To Our Team About Continuous Monitoring