Last updated: September 25, 2026
Talk To Rhythm360 About Your Operating Model
The cardiology RPM and RCM market segments into four operating models. Each model fits a different practice profile and assigns claim submission and denial cost differently.
Software-Only RPM fits solo practitioners and small EP clinics. The platform provides a dashboard, alert triage, and billing reports. Because the practice’s own staff reviews data daily, makes the monthly patient contact, documents time, and submits claims, the practice owns claim submission and denial cost entirely. Software-only vendors solve the visibility problem while leaving the staffing problem unchanged.
RPM Plus Billing/RCM Software fits mid-sized cardiology groups that have clinical staff but want automated CPT code capture and documentation support. The platform automates more of the billing workflow, yet the practice still owns denial appeals and audit exposure. A finalized report that never creates a charge in the EHR produces silent revenue loss. It generates no denial code, so no billing software catches it unless bi-directional write-back functions correctly.
Managed Clinical RPM Service fits practices without hiring capacity. The vendor runs day-to-day monitoring operations, including enrollment, data review, patient contact, and documentation, while the practice retains final billing responsibility and clinical direction. Fully managed clinical partners supply devices, software, and the clinical team, while the practice retains clinical ownership. Full-service RPM arrangements are commonly quoted at $40 to $80 per patient per month, which represents a substantial share of program revenue.
Enterprise RPM Infrastructure fits integrated health systems managing thousands of CIED and chronic-disease patients. These arrangements involve deep EHR integration, distinct regulatory frameworks, and often separate credentialing and facility enrollment requirements.
Rhythm360 by RhythmScience operates as a vendor-neutral CIED consolidation layer that makes any of these models billable. For cardiology practices that manage patients with pacemakers, ICDs, implantable loop recorders, and physiologic monitors alongside HF/HTN populations, Rhythm360 offers a practical starting point. Fragmented OEM data breaks billing workflows regardless of which operating model or RCM vendor a practice selects. Other platforms in this market include Murj, Implicity, Rhythm Management Group, and Octagos. Whichever model you choose, billing performance still depends on getting the CPT codes and monitoring cycles right, and the 2026 rule changes that code set.
See Which Operating Model Fits Your Practice
The CMS CY 2026 Physician Fee Schedule final rule (CMS-1832-F) added two new RPM codes effective January 1, 2026. CPT 99445 covers device supply with 2–15 days of transmitted data per 30-day period. CPT 99470 covers the first 10 minutes of RPM treatment management per calendar month. These join the existing codes 99453 (one-time setup), 99454 (device supply, 16+ data days), 99457 (first 20 minutes of management), and 99458 (each additional 20-minute increment).
The table below highlights the key billing risk for each code family. Focus on whether your platform can identify device type at ingestion and track the correct 30- or 90-day cycle, because CIED codes and RPM codes tend to fail for different reasons.
| Code(s) | Device Type | Cycle / Threshold | Platform Capability Required |
|---|---|---|---|
| 93294 (pacemaker professional), 93296 (pacemaker/ICD technical) | Pacemaker | 90-day cycle; not billable if monitoring period is under 30 days | Vendor-neutral CIED ingestion, 90-day period tracking, automatic charge release at period end |
| 93295 (ICD professional), 93296 (ICD technical) | ICD / CRT-D | 90-day cycle | Device-type identification at ingestion, ICD vs. pacemaker code routing |
| 93297 | Implantable cardiovascular physiologic monitor (e.g., CardioMEMS) | 30-day cycle; billable global, -26, or -TC | Hemodynamic data ingestion, 30-day period tracking, signed interpretation workflow |
| 93298 | Subcutaneous cardiac rhythm monitor / implantable loop recorder (ILR/ICM) | 30-day cycle; billable global, -26, or -TC | Rhythm data ingestion, ILR device-type flag, 30-day period tracking, signed interpretation workflow |
| 99453, 99454, 99445, 99457, 99458, 99470 | FDA-cleared physiologic monitors (BP, weight, glucose, pulse ox) | 99454: 16+ data days/30-day period; 99445: 2–15 data days; 99457: 20 min/month; 99470: 10 min/month | Automated transmission log, data-day counter, time-tracking, EHR write-back for billing evidence |
Device-Type Mismatch Risk Billing 93298 for a defibrillator patient is the most common device-mismatch error on this code. Remote ICD interrogation uses 93295 and 93296 on a 90-day interval. Conversely, 93297 is specific to implantable cardiovascular physiologic monitors such as pulmonary artery pressure sensors. It does not apply to loop recorders. A platform that fails to identify device type at ingestion will route claims to the wrong code family.
The 30-day transmission requirement for RPM device supply codes means data must be recorded and transmitted automatically by an FDA-cleared device. Manual patient entry does not qualify. Practices that pass RPM audits keep four items on file for every enrolled patient: automated transmission logs, proof of the device's FDA clearance, documented medical necessity, and a record of time spent on monthly management.
Before signing any vendor contract, collect written answers to the following questions. Verbal assurances during a demo rarely protect you during a payer audit.
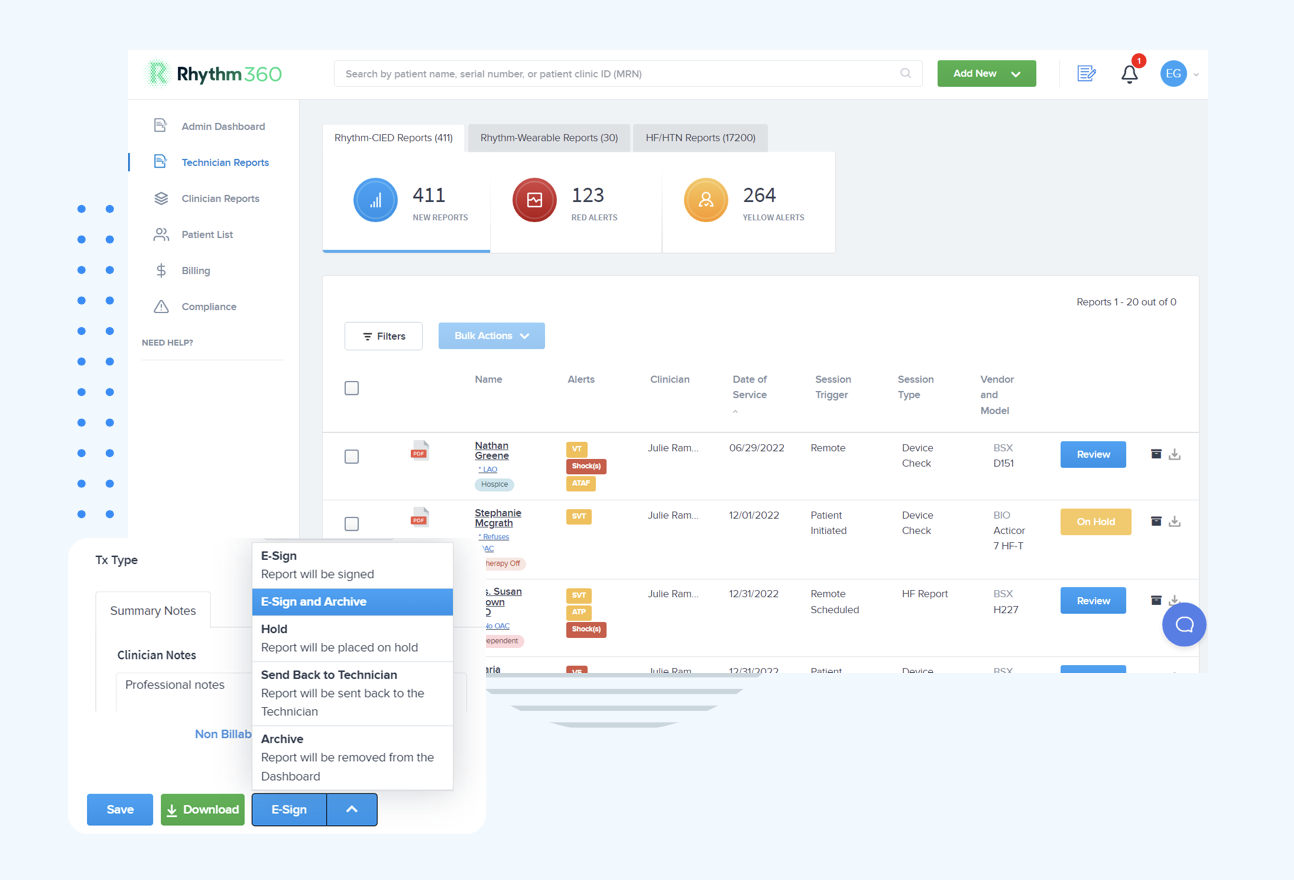
Rhythm360 does not manage or own revenue cycle management. It functions as a platform that improves billing and revenue outcomes through automated CPT code capture and documentation. Capabilities include automatic tracking of device-specific CPT pairings, 90-day and 30-day cycle management, and bi-directional EHR write-back that ensures finalized reports create charges instead of disappearing silently.
Remote patient monitoring introduces four operational failure modes that vendors often understate in sales materials.
Device Non-Transmission. Bluetooth-paired RPM devices require patients to keep both devices charged, in range, and correctly paired, which creates a real failure point for less tech-comfortable populations. Wi-Fi devices fail silently when a router password changes. Non-transmission below the 16-day threshold means 99454 cannot be billed for that period.
Staff Minutes Per Patient. A 2026 retrospective cohort study found that RPM patients required roughly 107 to 122 additional staff minutes per patient per year compared to usual care. Nursing time drove most of that increase. Without automated alert triage and guided workflows, that burden scales linearly with panel size.
Alert Fatigue. An analysis of the global Home Monitoring database including 11,624 patients reported more than 3 million alerts, with the majority originating from pacemakers and CRT-Ds. Fixed threshold-based alerting without AI triage produces non-actionable notifications that erode clinical attention to genuine events.
Documentation Audit Exposure. At audit, missing documentation for care management services is treated the same as services not rendered. A platform that generates a vendor printout rather than a physician-authored interpretation with a signed date fails to satisfy payer requirements for 93297 or 93298. The fix for that gap involves making the EHR the system of record, which bi-directional write-back supports.
Silent revenue loss starts upstream in the OEM portals. Once you understand how fragmented those feeds are in the next section, the fix becomes clear. Rhythm360 offers bi-directional EHR integration with Epic, Cerner, athenahealth, eClinicalWorks, and Greenway Health via HL7 so a finalized report always creates a charge.
A finalized report that never creates a charge in the EHR produces silent revenue loss. It creates no work queue item, no denial code, and no appeal opportunity, so the service simply never gets billed.
A practice administrator at a cardiology and electrophysiology group reported that remote device-monitoring reports were finalized in one platform but did not always create a charge in the EHR, resulting in 337 missed services and $22,600 in monthly collections lost before the gap was identified. Bi-directional write-back closes that gap by pushing finalized reports and billing triggers back into the EHR automatically.
Rhythm360 onboarding, including integration setup, typically takes a few days to a few weeks.
Fragmented OEM portals such as Medtronic CareLink, Boston Scientific LATITUDE, Abbott Merlin.net, and Biotronik Home Monitoring break billing workflows regardless of which RCM vendor a practice selects. Each portal formats transmission reports differently, which complicates the operational task of pulling 99457/99458 time documentation. Staff logging into four separate portals to reconcile monitoring periods, device types, and transmission dates before submitting claims introduces the exact errors that generate the most common denial categories, including wrong device code, early submission, and missing signed interpretation.
Rhythm360 ingests and normalizes disparate data streams via API, HL7, XML, and PDF parsing with computer vision. Redundant data feeds and AI-powered extrapolation push transmissibility above 99.9%. The University of Chicago Medicine reviewed more than 73,000 reports annually through Rhythm360 in calendar year 2025, averaging more than 18,000 reports per quarter, with clinicians reporting improved billing and accountability following implementation. As Andrew Beaser, MD, Associate Professor of Medicine at UCM, noted, “We are able to address these issues earlier; rather than waiting for a 3-month visit, we can call patients in for evaluation.”
The following table shows how Rhythm360 maps to the four operating models described earlier and clarifies who owns claim submission in each scenario.
| Operating Model | Rhythm360 Role | Who Owns Claim Submission | Key Rhythm360 Capability |
|---|---|---|---|
| Software-Only RPM | CIED + HF/HTN data consolidation layer, automated CPT code capture | Practice | Vendor-neutral ingestion, automated billing documentation, EHR write-back |
| RPM Plus Billing/RCM Software | Upstream data normalization feeding downstream billing platform | Practice (with billing software support) | Device-type identification, 30/90-day cycle tracking, charge trigger automation |
| Managed Clinical RPM Service | Data infrastructure enabling managed service operations | Practice (vendor prepares billing file) | AI alert triage, CCT oversight option, HIPAA-compliant mobile access |
| Enterprise RPM Infrastructure | Enterprise-scale CIED consolidation with deep EHR integration | Health system billing department | HL7/API/XML ingestion at scale, bi-directional Epic/Cerner integration, >99.9% transmissibility |
Map Rhythm360 To Your Billing Workflow
A 90-day pilot with 50–100 patients produces enough data to evaluate platform performance before full deployment. Structure the pilot around three metrics that predict program economics at scale.
At the end of 90 days, compare pilot results against the written RFP answers each vendor provided before the demo. Gaps between promised and actual denial rates, charge capture rates, and staff time provide the clearest signal of operating model fit.
Profitability depends on four cost drivers: vendor fee per patient per month, staff minutes per patient, denial rate by code family, and device transmission compliance rate. A practice paying $40–$80 per patient per month to a full-service vendor while billing roughly $120–$160 in RPM codes operates on a margin that depends heavily on denial rates and transmission compliance. Practices with in-house staff and automated platforms typically retain more margin when the platform eliminates the manual reconciliation burden that drives staff cost.
Medicare pays for RPM under the Physician Fee Schedule when services meet CMS coverage requirements. These include an established patient relationship, an FDA-cleared connected device, documented medical necessity, patient consent, and transmission thresholds met within the billing period. Medicare Advantage plans generally follow Medicare rules but may impose prior authorization requirements that differ by plan. Commercial payers have separate coverage policies that staff must verify at enrollment. The practice bills and collects. The vendor does not receive Medicare payment directly unless the practice has assigned billing rights.
CMS requires an established patient-provider relationship before RPM services begin and patient consent documented before billing. The device must be FDA-cleared and transmit data automatically, since manual entry does not qualify. Documented clinical staff time is required for management codes. CPT 99454 requires at least 16 days of transmitted data per 30-day period, and CPT 99445 covers 2–15 days. CPT 99457 requires at least 20 minutes of treatment management time per calendar month, including one live interactive communication. Documentation must include transmission logs, time records, and a care plan accessible to the care team.
As covered earlier, 99445 covers device supply at 2–15 data days and 99470 covers the first 10 minutes of management. The key detail for billing is mutual exclusivity. 99445 and 99454 cannot both be billed for the same patient in the same period, and 99470 and 99457 cannot both be billed once total management time reaches 20 minutes. The existing codes 99453, 99454, 99457, and 99458 remain in effect in 2026, with 99453 updated to be explicitly an initial-service code.
The core problem facing cardiology practice administrators evaluating RPM and RCM platforms centers on operating model alignment rather than feature comparison. A software-only platform handed to a practice without clinical staff capacity produces the same outcome as a managed service handed to a practice that needs clinical control: revenue leakage, denial exposure, and staff burnout.
Rhythm360 is the consolidation layer described above. It eliminates the upstream data fragmentation that breaks billing workflows regardless of which RCM vendor or operating model a practice selects. Practices implementing Rhythm360 have achieved up to a 300% increase in revenue capture and up to an 80% reduction in critical alert response times.
Use the operating model framework and the five ownership questions in “Who Owns What In The Revenue Cycle” to interrogate every vendor on your demo schedule. Require written answers. Run the 90-day pilot. Measure denial rates and staff minutes rather than the quality of the demo.
Schedule A Rhythm360 Pilot Review